
Alternative Skin Cancer Treatments That Are Working
By Alicia Cashman
Nov. 20, 2026
I’ve been treating various skin cancers on my body for about 10 years. This does not make me a doctor nor an expert, just an informed friend who’s read a lot and experienced more. Any information in this article is purely educational and from my own experience and is not intended as diagnosis or medical advice.
Due to this unwanted pilgrimage, I’ve been experimenting upon myself – a common trait amongst Lyme/MSIDS patients, which is why I love support group, where you can learn more in a couple hours chatting with fellow patients than you can by getting a four year college degree.
Of course my cancer spots were initially located around my eye. You know, the really thin, sensitive skin required for blinking and believe it or not can affect tear production?
Because I initially had no experience whatsoever, I made an appointment with a dermatologist who from a biopsy, diagnosed me with basal cell carcinoma. I was told MOHS surgery is the best, so that’s what I had done. MOHS was named after Dr. Fred Mohs, the man who invented it. Supposedly cure rates of 99% can be achieved.
The procedure involves:
- Surgeon removes the visible part of the cancer along with small margin of surrounding healthy tissue.
- While the patient waits the surgeon examines the tissue for cancer cells by taking the specimen to an on-site laboratory, using special ink to color the margins, sectioning the sample, placing the sections on microscope slides, and evaluating the slides for any residual cancer.
- Depending on the results of the analysis the surgeon determines where to remove tissue next only removing tissue containing cancer.
- The process repeats until all cancerous tissue has been removed.
This means that the patient sits in a chair waiting upon pathology results. If there are remaining cancer cells they continue digging until none remain.
And this is what it looks like:
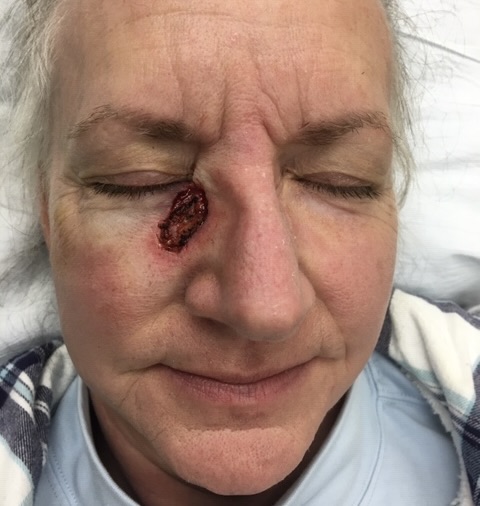
And yes, it hurt like hell.
Of course they numb it for surgery but when you get home…..wowza. It takes a solid month to heal and you must keep it wet and open to send all who see it shrieking away. I probably didn’t help with the pain because I’m always meddling, but I knew there was no way I was going to have plastic surgery, which was what they recommended. After undergoing the scalpel, I announced, “Send me home! I’ll deal with this myself!” So they did.
What I knew that they didn’t is that olive oil infused with infused ozone was going to put oxygen into all those cells and tissue and would result in skin like a baby’s. And that’s exactly what happened.
Here’s what that looked like:
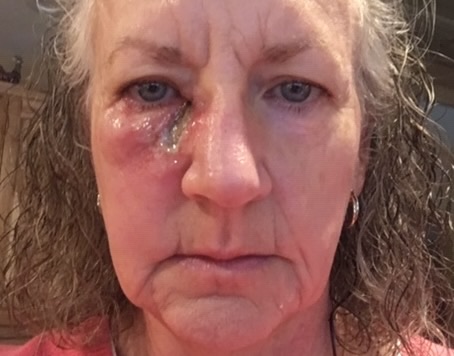
I want you to notice how the reddened surrounding skin due to the ozone which went to work and began doing what it does: infuses tissues with O3. But for me, due to the location, the ointment would thin and get into my eye which did sting, but I knew I had to stay the course – that it would be worth it in the end. And it was.
Here’s a few more pics to show the progression:
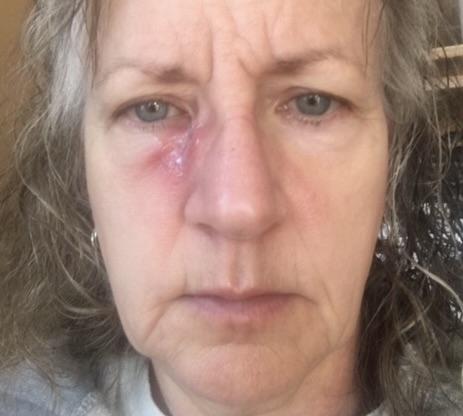
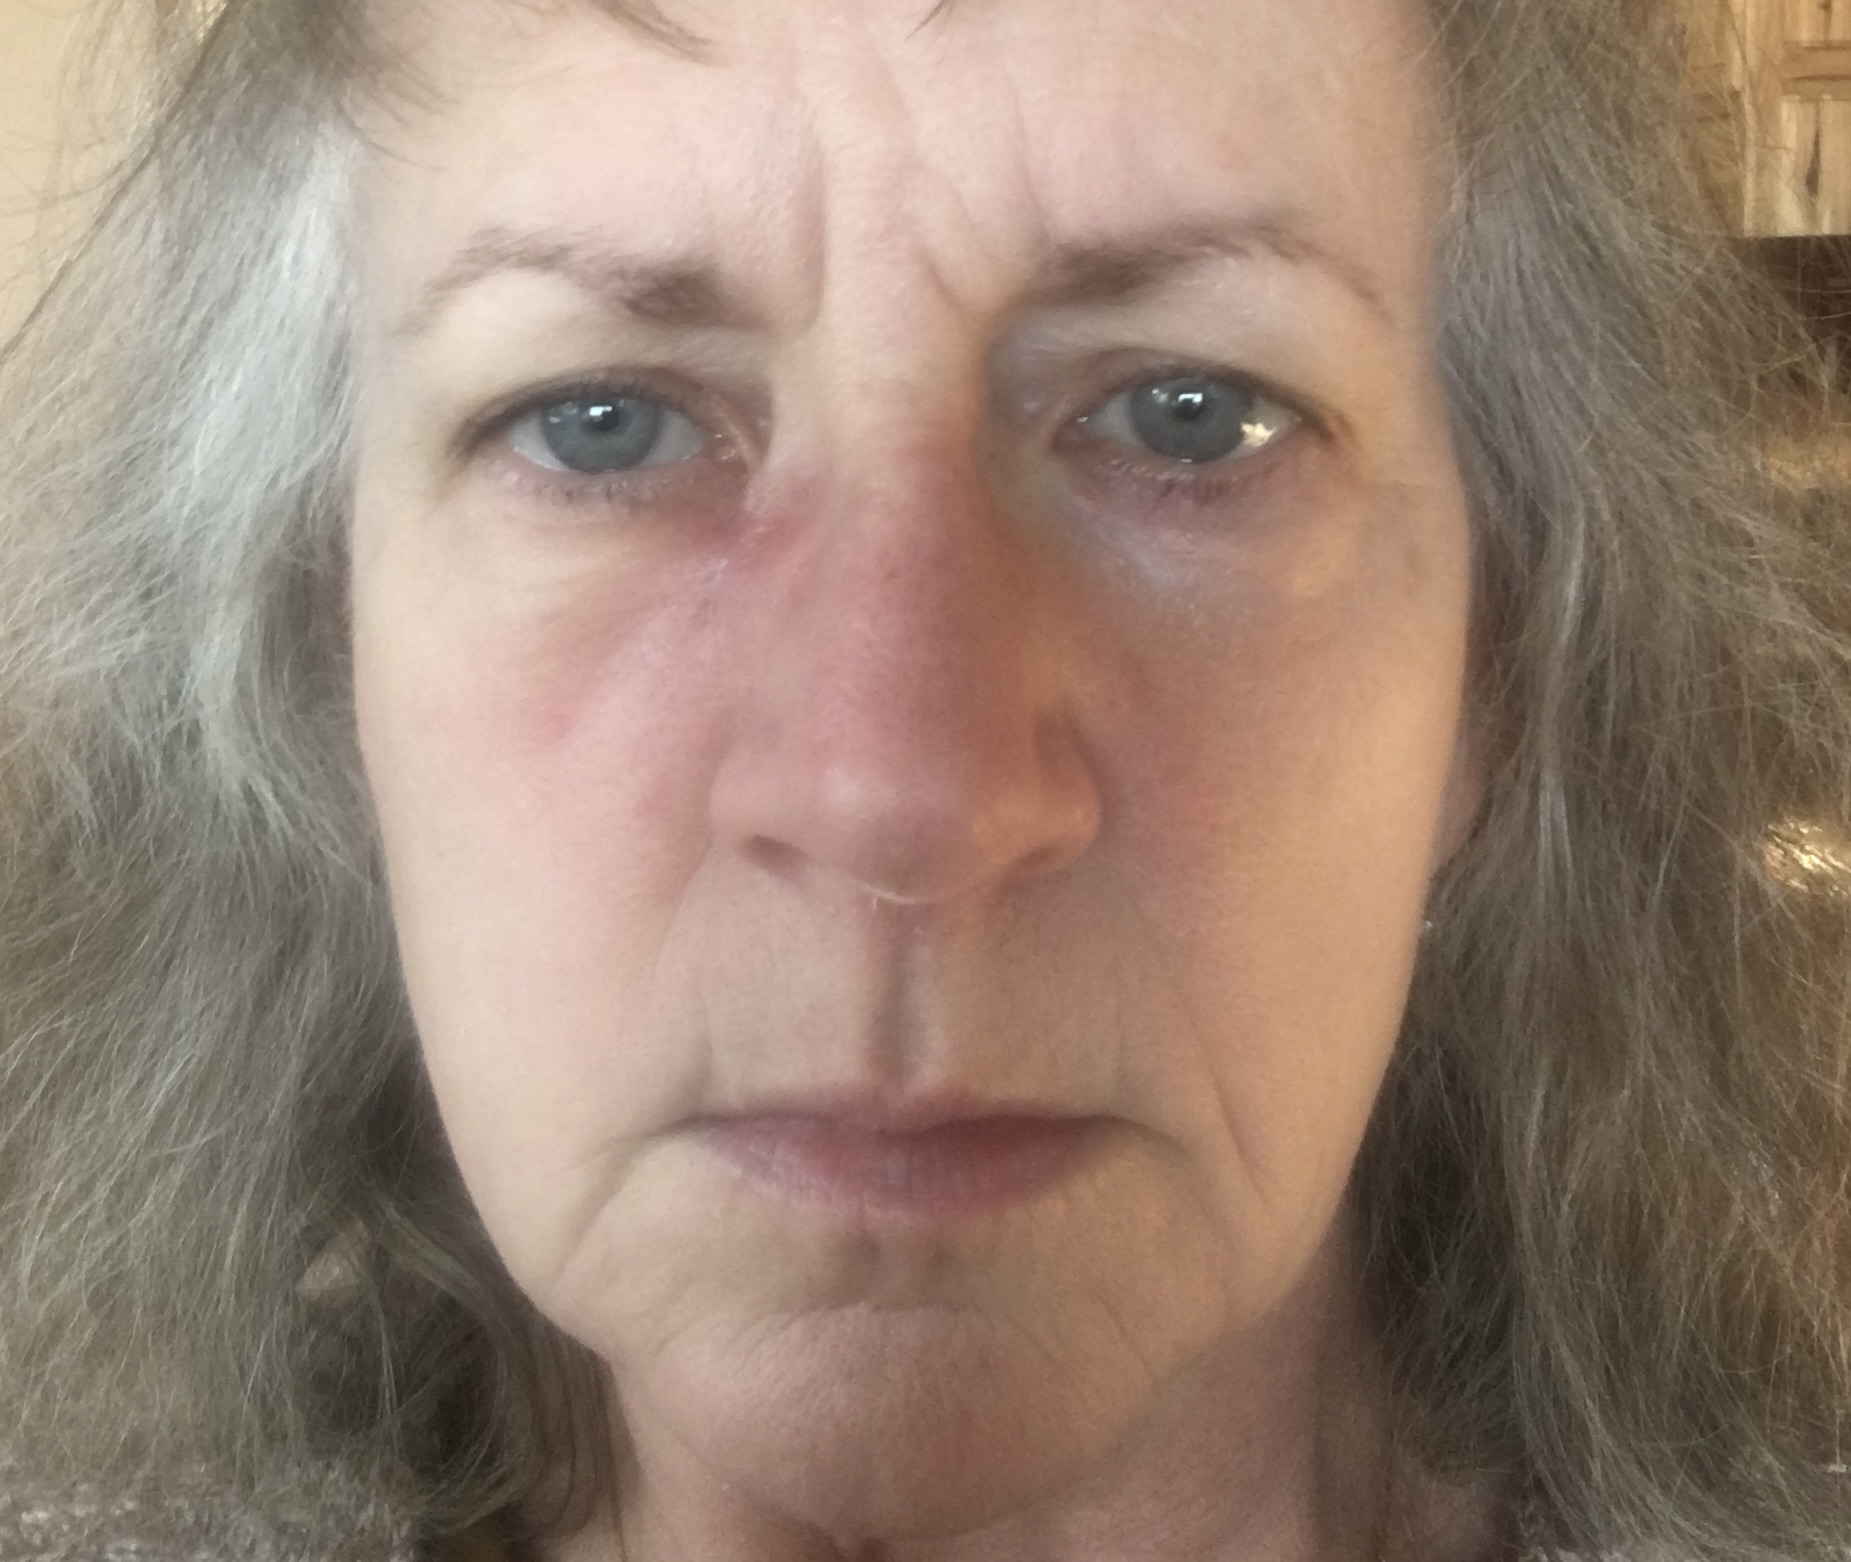
Now, even the redness is gone and all that remains is a very, very small scar.
Fast forward: the very same thing happened on the other side of my face. I had MOHS again with similar results, but the second spot was deeper. Both times the doctors suggested plastic surgery and both times I responded, “Nope, send me home.” I try and avoid pain when I can and I had experience under my belt this time so I forged ahead with my plan of ozonated olive oil on my own at home. They normally recommend petroleum jelly, which I sometimes placed over the ozonated olive oil to hold it all in place.
I must add that both the dermatologist and the plastic surgeon were impressed by the results and agreed no further surgery was needed, and I saved thousands of dollars and pain.
When I met Dr. Rowan, aka, king of ozone at a conference, I told him about my experience. He wanted me to send him pictures and what I did. He made this into a video you can watch here to see the entire progression:
By now I was educated in knowing what to look for so when a tiny scab on my leg I had for years wouldn’t heal along with a few other suspicious spots around my nose, I took action. This time I didn’t head to the dermatologist but instead followed the advice of my Lyme doctor who recommended CURADERM BEC5 – an egg plant derivative with salicylic acid. Curaderm targets the cancer cells and destroys them while the salicylic acid sloughs the old dead skin away. Directions here. It will not target normal cells.
In my case, the cancer on my inner thigh was deep which became painfully pussy at times during CURADERM treatment. Eventually it’s quite obvious that as the old, dead skin sloughs off, new virgin skin rises to the top. I won’t lie: it can be extremely painful depending upon how deep it is and mine was deep. It’s important to take a wet wash cloth and soap to help remove the dead skin and then reapply CURADERM and cover the area with occlusive tape.
Apply twice a day (morning and night) until lesions are completely gone and are replaced with normal skin. Word of warning: the tape sticks fast and can pull skin off when you remove it. This also is painful. At times I would cut bits of sterile gauze to put over these sensitive areas before covering with tape. This stopped the skin from pulling. I know the directions state not to do that but extreme times call for extreme measures. There is a skin colored tape and a white tape. I found the white tape to be more gentle, albeit more noticeable. How much are you willing to suffer for vanity?! I’m sure this all depends upon the manufacturer and can vary from product to product so is not a hard and fast rule.
Now for the bad news: it costs $200 for a tiny tube.
I don’t have a picture of the initial scab but there was definitely an ice-berg effect. The CURADERM sought out cancer cells and my initial tiny scab became this:
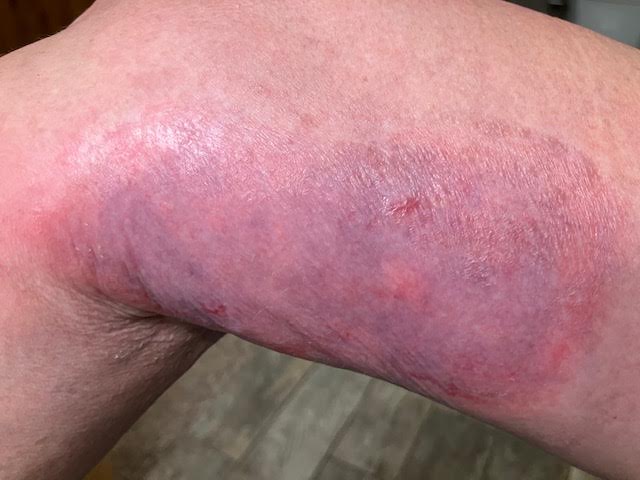
And yes, it hurt to the point of crying. There were pussy spots and every time I applied the product or wiped it off, the salicylic ACID exposed the red virgin skin underneath. But, when I ponder how disfiguring a MOHS surgery could have been, I stiffen my upper lip and trod on.
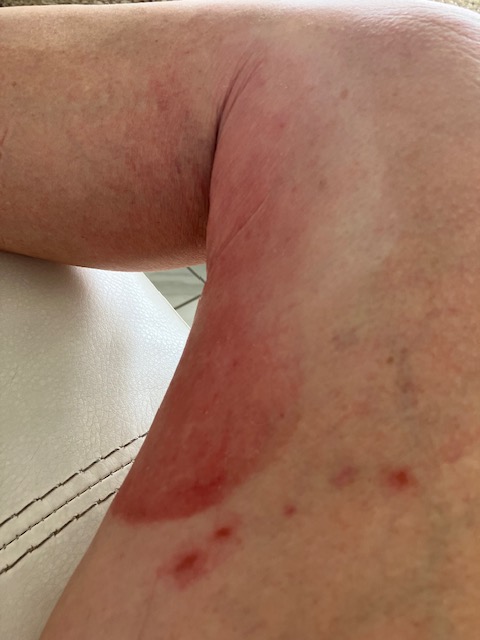
Here’s a picture of the spots after removing the tape. Now this is important: these red, painful spots were cancerous, the tape only exposed the cancer that was there already, showing me I needed to expand coverage of the treatment. The tape will not do this to normal skin.
By this point I was reading and listening to all I could find on skin cancer. Besides finding out many experts believe seed oils are causing the record numbers of skin cancer (and other cancers), that dermatology reinvented itself as a cancer specialty and is behind the disastrous war against the sun, and that sunscreens are in fact linked to cancer, I heard from a cancer doctor who started speaking about the successful results of many using ivermectin paste on all sorts of skin cancers – and other inflammatory skin conditions (eczema, cystic acne, rosacea, psoriasis, etc.)
I was pretty desperate to find something that didn’t hurt like the dickens.
Let me be clear on a point: it is believed the seed oils sensitize your skin to the sun. It’s not that the sun isn’t involved, it’s that the root issue needs to be dealt with. Also, the relatively benign skin cancers are implicated to sun exposure, while the ones responsible for most DEATHS are due to lack of sunlight. So dermatology’s advice to stay out of the sun is not sound.
Without anyone telling me what to do, I derived my own treatment out of necessity. I would apply ivermectin morning and night and then 1-3 times a week I would use CURADERM to slough off the dead skin. The reason I feel both products are needed is because CURADERM makes it obvious where the cancer is. It literally hunts it down. It also exposes the red skin, allowing you to visualize where you should be applying the creams. I’m not certain this would have happened using ivermectin alone. I also discovered that Panacur (Fendbendazole) works as well if not better. It’s a 10% paste vs. the 1.87% ivermectin paste. I started rotating these as well.
The ivermectin I use is a gel that stays wet requiring either a bandage(s) or I folded up a bandana and taped it on my leg (I got tired of buying huge bandaids). The Panacur; however, will dry eventually so you don’t have to cover the skin unless you don’t have time to let it dry. Anyway, if I’ve learned anything from Lyme/MSIDS it’s that layering treatment tends to cover all the bases more thoroughly.
Here’s a more recent picture of my leg:
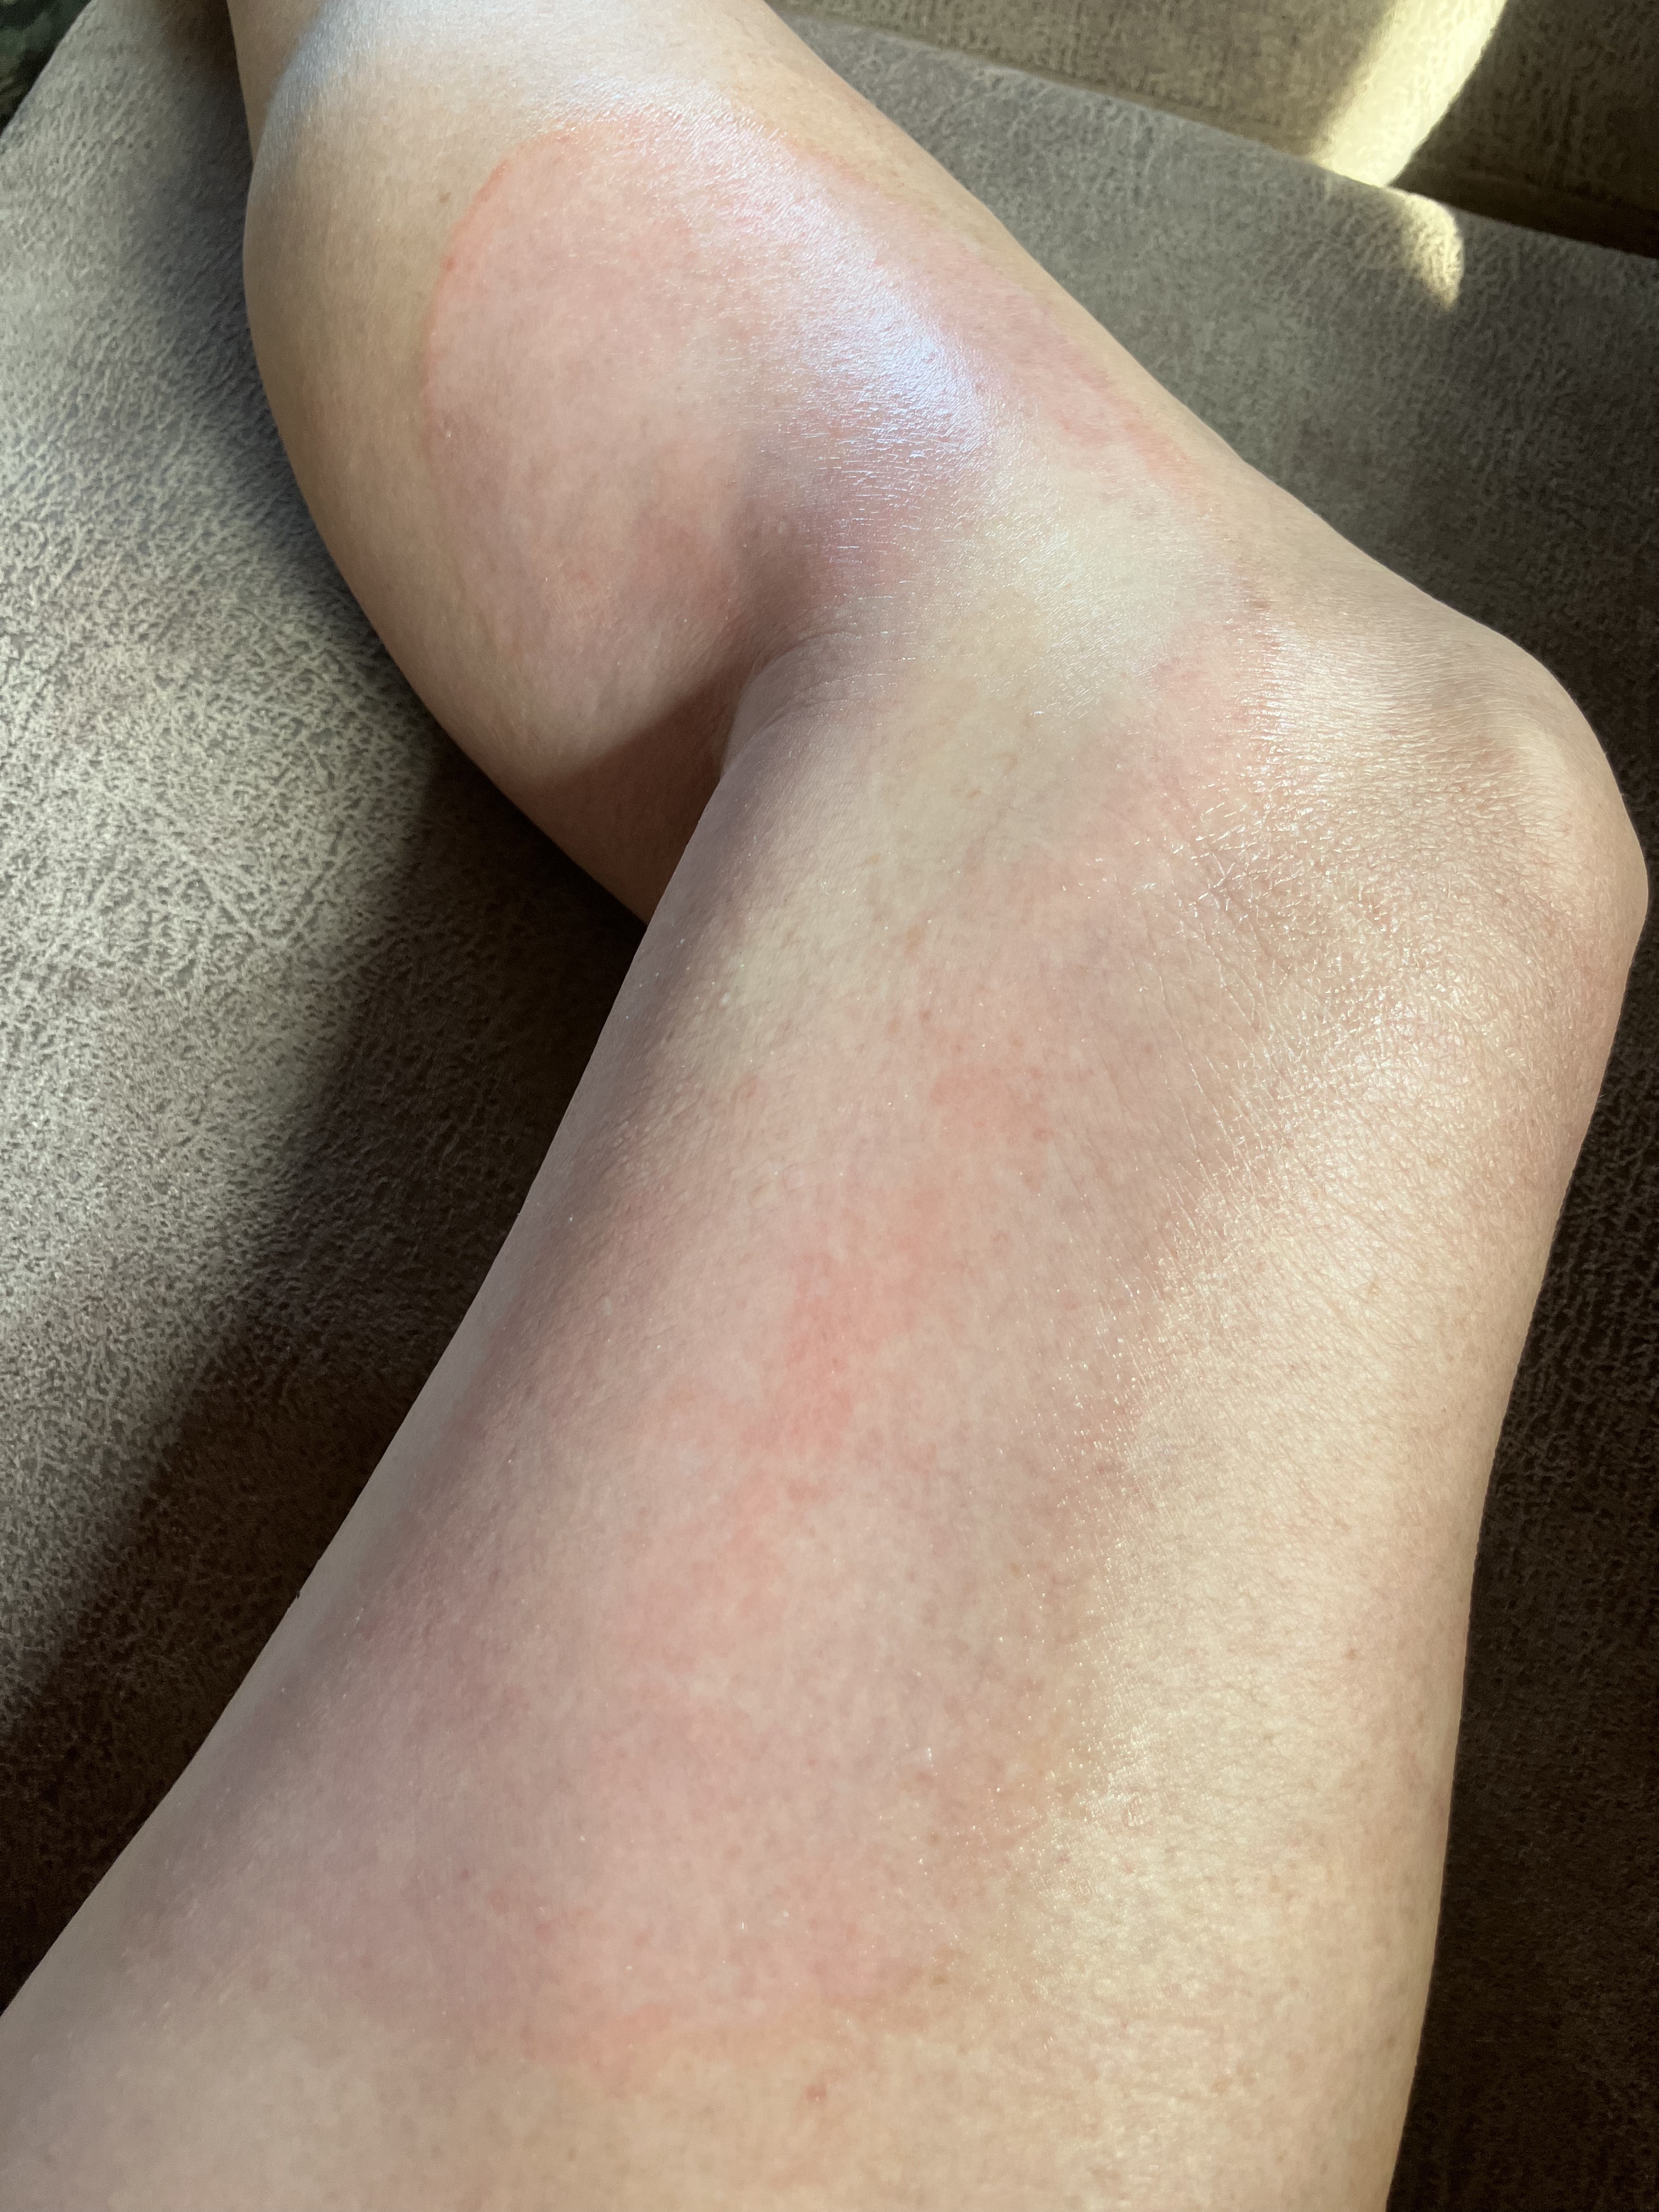
It is obvious where the cancer remains. Note how it is much, much larger than what is shown from the initial picture, but there are white areas (cancer free) as well and it’s obviously not as deep. It also barely stings now after CURADERM, which shows me we are getting close now, but it’s taken a full year, and I’m as consistent as a pendulum on a clock with treatments! Now ponder what I’d look like if they cut this out.
This picture of my face also shows how the CURADERM seeks out the cancer. The red spot on the left shows a deeper cancer but the rest is fairly superficial.
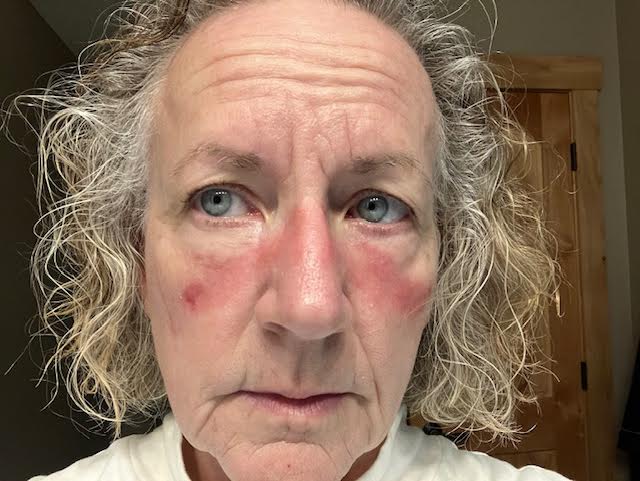
I’ve been done with my face for a while; however, if there’s a tiny sore starting or anything open I immediately put ivermectin or Panacur on it at night. It usually goes away after a few applications. If I’m going to be home all day, I’ll apply it twice to expedite matters.
All of this brings me to a third treatment for skin cancer: vitamin C and DMSO.
A Midwestern Doctor took the topic on. DMSO’s potent mechanisms of action (e.g., being anti-inflammatory, improving circulation, rescuing cells trapped in the cell danger response, and stabilizing proteins) underlie many dermatologic conditions, including skin cancer.
The treatment includes 30% ascorbic acid in a 95% DMSO solution mixed with 5% water applied twice a day for about 8-12 weeks in the studies (although I must surmise this depends upon the depth of the cancer). A study utilizing this therapy showed over 86% of basal cell carcinomas disappeared. In those with squamous cell lesions, 56% disappeared while the remaining 44% showed an 85% reduction in size. 94% of participants avoided surgical excision. Listen to Nicolas Hulscher, MPH discuss the treatment and study.
And just in May of this year, a systematic scoping review on topical vitamin C for the prevention and treatment of actinic keratoses and nonmelanoma skin cancers found that highly concentrated topical formulations of vitamin C may have some benefit in the treatment of AKs and low-risk subtypes of non-melanoma skin cancers.
A previous study found high-dose vitamin C therapy has the definite potential to provide beneficial and cost-effective anti-cancer treatment options that should be investigated further. Ascorbic acid may become a significant treatment option in the fight against cancer, due to its widespread availability in nature, minimal toxicity, and low cost.
Please note that this was without DMSO, a well known and long used penetrating agent that safely and cheaply does about a million things. So the addition of DMSO allows for a lower vitamin C dose due to it’s penetration into the cells.
This may become my new experiment.
I’ll update you when I have more results.
For more on cancer:
- https://madisonarealymesupportgroup.com/2026/04/10/1-in-3-cancer-free-ivermectin-trial-stuns-but-reset-5-aims-even-higher/
- https://madisonarealymesupportgroup.com/2026/04/10/a-new-ivermectin-mebendazole-cocktail-for-cancer-treatment/ Many more links after article.
- https://madisonarealymesupportgroup.com/2026/01/05/preventing-cancer-the-root-protocols/
- https://madisonarealymesupportgroup.com/2024/10/15/first-cancer-protocol-using-ivermectin-mebendazole-and-fenbendazole-published/
- https://madisonarealymesupportgroup.com/2025/02/07/cancer-disappeared/
- https://madisonarealymesupportgroup.com/2025/08/05/cancer-is-reversible-prof-flavins-50-years-of-research/
- https://madisonarealymesupportgroup.com/2025/11/03/tenenbaum-cancer-protocol/
- https://madisonarealymesupportgroup.com/2025/09/03/highlights-how-fenben-and-meben-disrupt-cancer-pathways/ Within link is an interview with Professor Thomas N. Seyfried, PhD whom was so instrumental to Tenenbaum’s treatment. Also included is Joe Tippen’s cancer protocol.
- https://madisonarealymesupportgroup.com/2025/03/07/metabolic-therapies-reclaiming-cancers-achilles-heel-through-the-ivermectin-fenben-and-allulose-revolution/
- https://madisonarealymesupportgroup.com/2024/10/23/alternative-cancer-treatments-18-proven-interventions/
- https://madisonarealymesupportgroup.com/2026/01/12/reduce-cancer-risk-by-90-using-evidence-based-natural-compounds/






